




Introduction
For many healthcare practices, denied claims and prolonged A/R cycles are silent profit killers. They lead to unpredictable revenue, staff burnout, and operational burden. According to HFMA, 22% of healthcare leaders report losing at least $500,000 annually to denials, while 1 in 10 loses over $2 million each year.
You submit claims every day, expecting steady reimbursements, but somehow the denials keep piling up. In 2026, medical claim denial rates are rising across the U.S., driven by stricter payer edits, automation, and tighter prior authorization enforcement.
Experian Health’s 2025 State of Claims Survey found that 41% of healthcare providers reported claim denial rates of 10% or higher.
If you’re looking to understand why denials occur, how they affect your revenue, and what steps you can take to fix them, you’re in the right place. This guide follows a structured approach: why denials happen, how to fix them, and how to prevent them permanently.
What Is Denial Management in Medical Billing
Denial management is a core component of revenue cycle management. It identifies, corrects, and prevents claim denials, supporting accurate billing and consistent cash flow.
Key Trends Driving Denials in 2026
- Stricter payer edits: Automated systems reject claims for minor mismatches more aggressively.
- Prior authorization enforcement: Payers require verification; missing approvals trigger automatic rejections.
- AI-powered audits by payers: Algorithms identify coding or coverage issues before human review.
- Telehealth and remote services: New modifiers and codes create opportunities for claim errors.
- Gold card programs: Medicare Advantage and commercial payers reward low-denial providers. Non-compliant practices face stricter scrutiny.
How Denial Management Protects Revenue
Nearly 1 in 5 in-network claims were denied in 2023, according to KFF. Denial management services address these revenue leaks by:
- Capturing lost revenue: A large share of denied claims are never reworked or resubmitted because of administrative backlogs and short payer deadlines. A structured workflow helps ensure claims are corrected and resubmitted.
- Reducing rework costs: Denied claims cost $43.84 each to reprocess. Addressing root causes reduces repeated errors and saves time and money.
- Accelerating AR recovery services: Faster resubmissions and focused follow-up support AR recovery services and improve the collection cycle.
- Preventing recurring denials: Identifying patterns in coding, eligibility, or documentation helps prevent future denials.
- Optimizing staff time: Automation and clear workflows allow staff to focus on higher-value activities rather than repetitive follow-up.
Common Causes of Medical Claim Denials
Incomplete or Incorrect Information
Errors in patient demographics, insurance ID, NPI, claim formatting, or modifiers remain common denial triggers. Even a misspelled name or missing modifier can lead to rejection.
Eligibility and Coverage Issues
Submitting claims for patients who are not eligible or whose coverage has expired can lead to denials. Eligibility verification before the visit can prevent many of these errors.
Lack of Prior Authorization
Many payers require prior authorization for specific procedures or medications. Missing or outdated approvals can lead to claim denials even when the service was medically necessary.
Out-of-Network Services
Claims for services provided outside the patient’s insurance network are often denied or reimbursed at lower rates. Clear communication about network status can reduce disputes and denials.
Duplicate Claims
Submitting the same claim multiple times can flag it as a duplicate and lead to denial. Automation tools can help detect and prevent duplicate submissions.
Medical Necessity Denials
When documentation does not clearly support the need for a service or test, payers may classify it as not medically necessary. Detailed clinical documentation helps justify treatment decisions.
Coding and Documentation Issues
Incorrect or outdated CPT, ICD-10, or HCPCS codes and incomplete notes are common causes. Regular coding audits and staff training support first-pass accuracy.
Timely Filing Limits
Each payer has claim-submission deadlines. Missing those timelines can result in denials that are difficult to reverse.
Bundling and Unbundling Errors
Submitting multiple claims for procedures that should be billed together, or failing to bundle them correctly, can trigger payer edits.
Coordination of Benefits Issues
When a patient has multiple insurance plans, confusion about the primary payer often causes denials. Proper verification at registration can prevent COB-related issues.
What the Data Shows About Denials
A KFF analysis of 2023 HealthCare.gov marketplace claims reported the following reasons among denied in-network claims where reason data were available:
Denial reason | Share |
|---|---|
Other reasons | 34% |
Administrative issues | 18% |
Excluded services | 16% |
Exceeding benefit limits | 12% |
Missing prior authorization or referral | 9% |
Lack of medical necessity | 6% |
Types of Denials
Hard denials are non-payable and typically require appeals, often involving medical necessity or coding and documentation issues. Soft denials are temporary and may be corrected and resubmitted. Knowing the difference helps teams prioritize recoverable claims.
In-Network and Out-of-Network Claim Denials
Not all denials are operational mistakes; some are tied to contractual or network limitations.
In-Network Denials
Common causes include missing authorization, invalid eligibility, non-covered benefits, and late filing. In-network claims can still be denied when internal workflows do not meet payer requirements.
Out-of-Network Denials
These may occur when a plan excludes out-of-network benefits, applies contractual carve-outs, or classifies a procedure as non-emergent. Upfront patient communication is important for reducing disputes.
Top Denial Codes to Track
Claim Adjustment Reason Codes and Remittance Advice Remark Codes help explain payer adjustments and denials. Verify the current description through X12’s code lists and the payer’s remittance advice before correcting or appealing a claim. For a focused overview, see 5 Claim Denial Codes Small Practices Should Understand.
- CO-16: Claim or service lacks information or contains submission or billing errors
- CO-22: Care may be covered by another payer under coordination of benefits
- CO-109: Claim or service is not covered by this payer and must be sent to the correct payer
- PR-1: Deductible amount
- PR-204: Service, equipment, or drug is not covered under the patient’s current benefit plan
- CO-50: Service is not covered because the payer does not deem it medically necessary
How to Recover Denied Claims Revenue
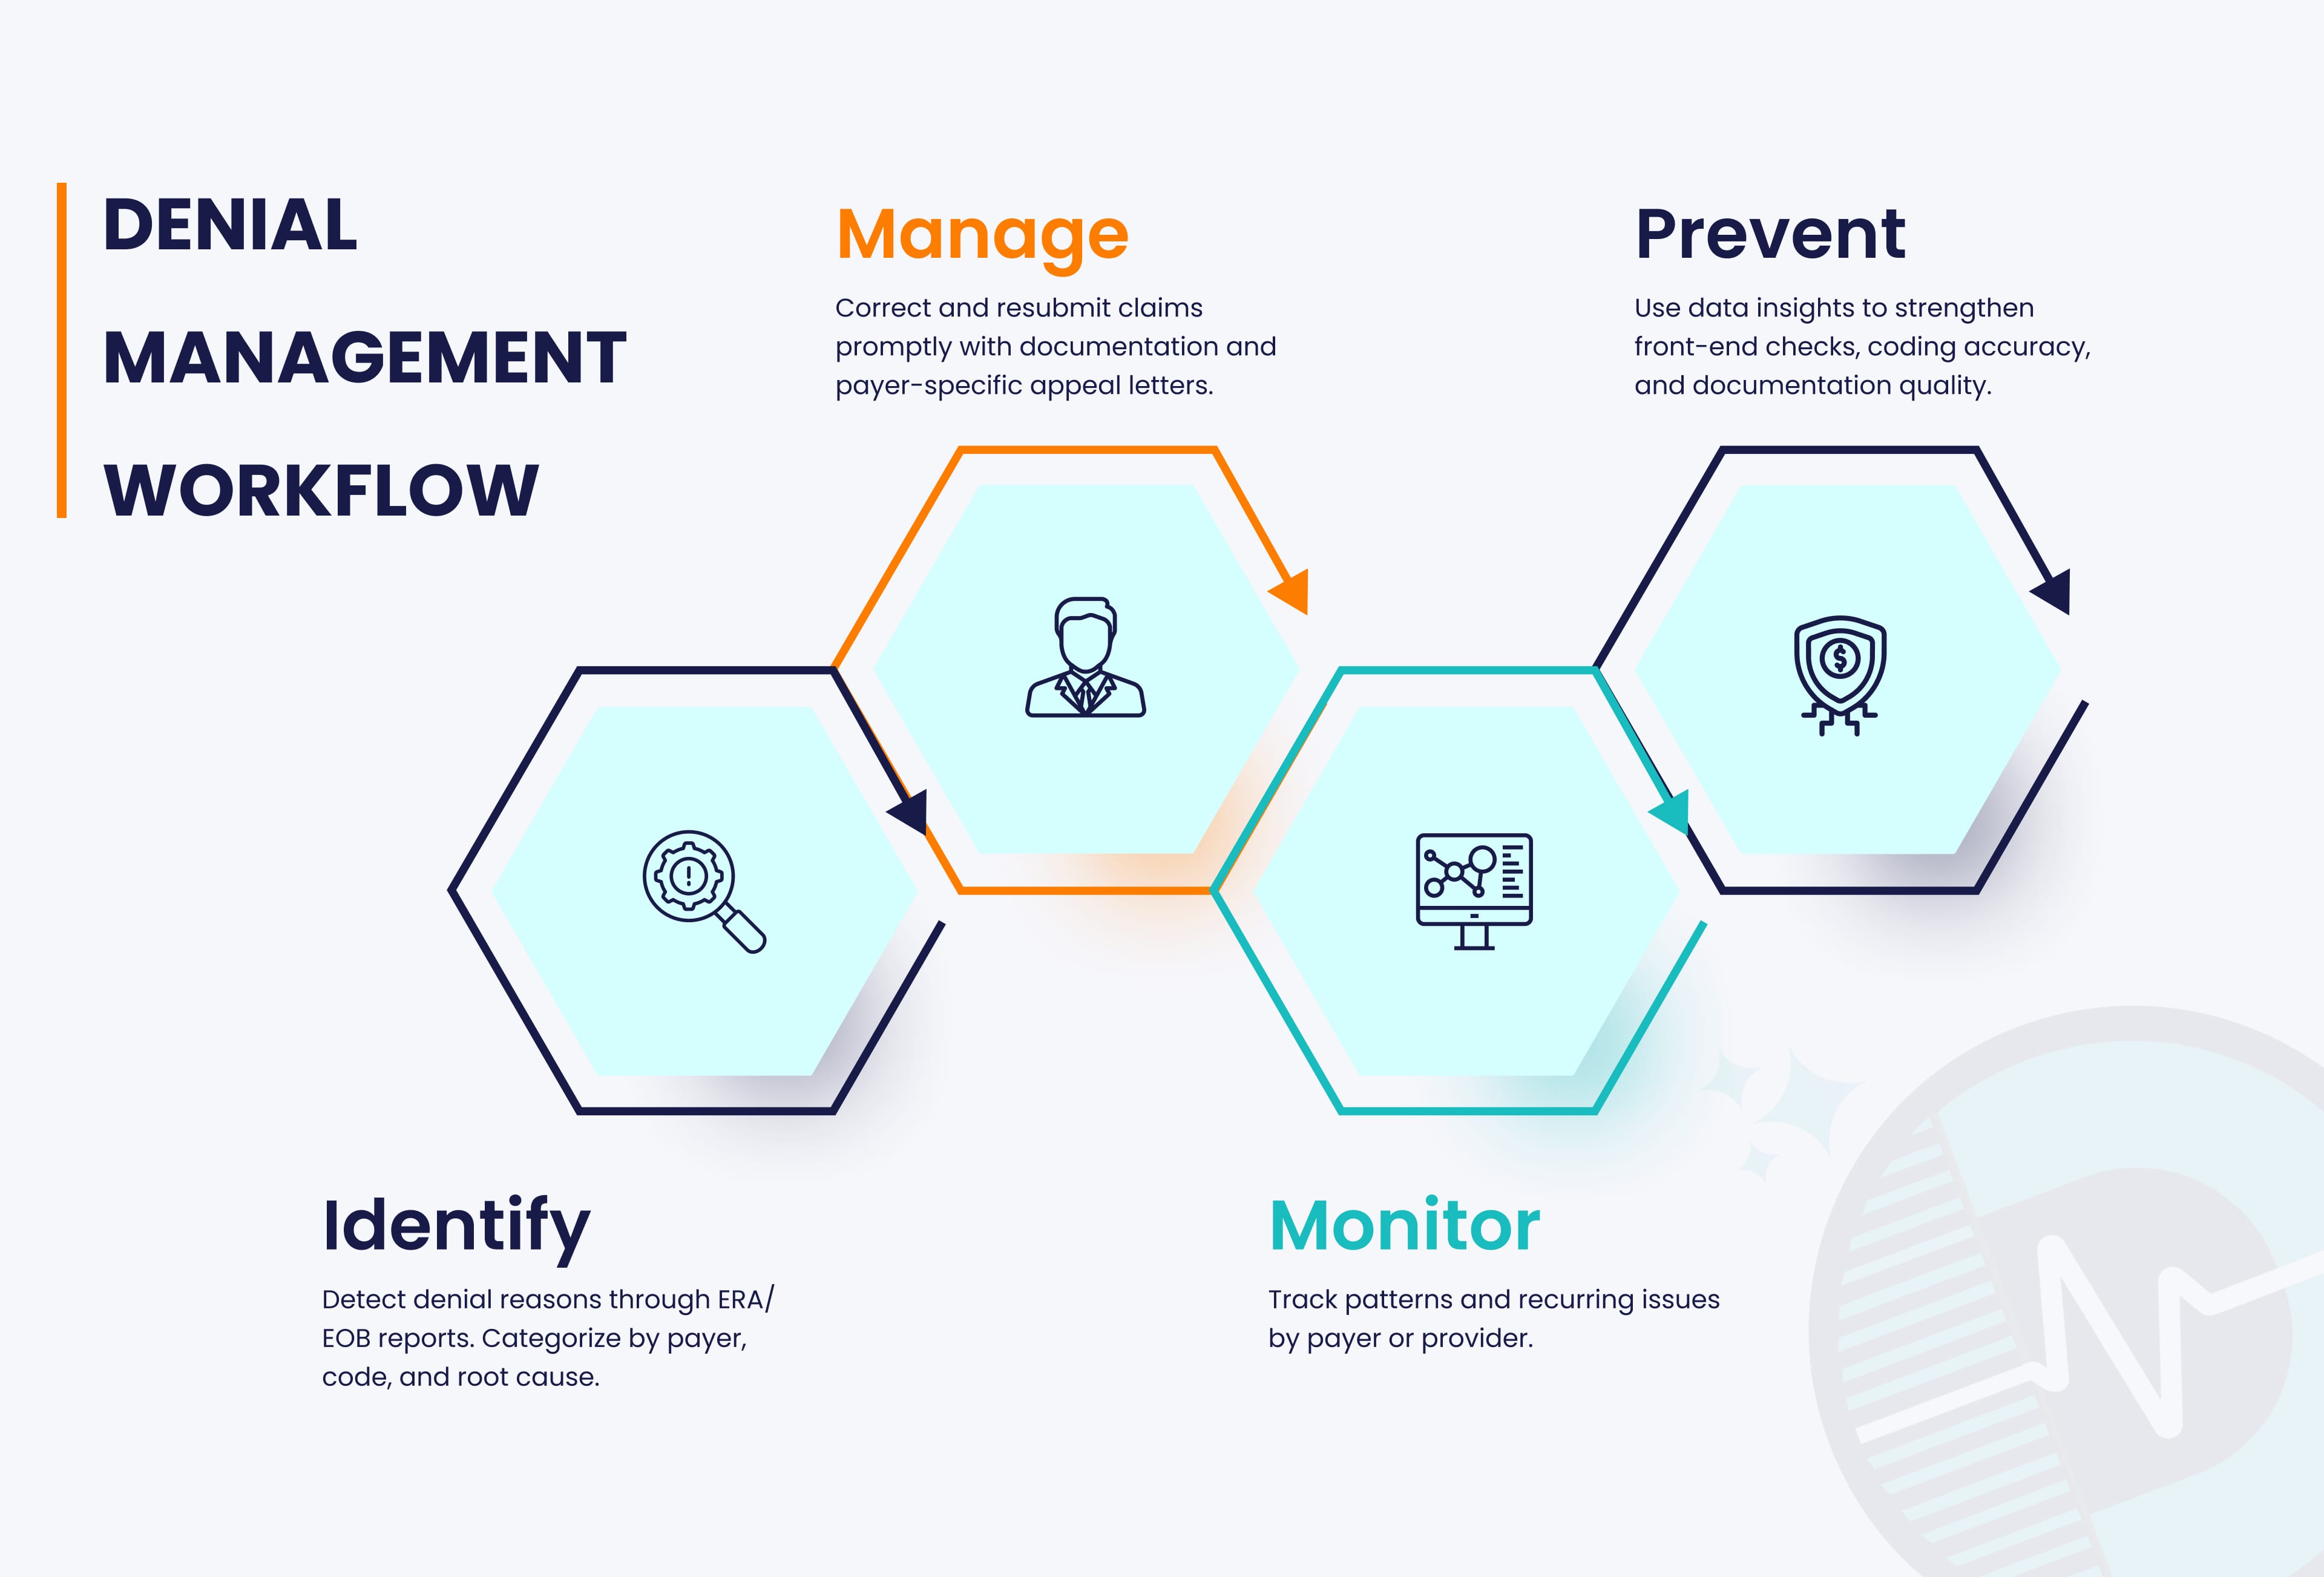
Identify denied claims early
Monitor claim status through your clearinghouse or practice management system so denials are flagged as soon as they occur.
Categorize denials by root cause
Group denials into eligibility and coverage issues, coding errors, prior authorization gaps, administrative mistakes, and medical necessity denials.
Correct errors and resubmit quickly
Update patient demographics, correct codes, add missing modifiers, and verify authorization details. Delayed resubmissions may fall outside payer filing limits.
Appeal high-value claims strategically
Respond to the specific denial reason, reference the applicable payer policy or Local Coverage Determination when relevant, and attach supporting clinical documentation.
Track trends to prevent future denials
Analyze denial data by payer, provider, and service type to identify recurring issues and improve first-pass claim performance.
Proven Strategies to Prevent Denials
According to AHIMA, effective denial management focuses on prevention and a structured approach to resolution.

- Front-end accuracy: Verify demographics, eligibility, and authorizations before the visit.
- Ongoing training: Keep billing and coding staff current on payer rules and coding requirements.
- Track KPIs: Monitor denial rates, clean claim rates, and days in A/R.
- Leverage automation: Use claim-scrubbing and workflow tools to flag incomplete or high-risk claims.
- Collaborate with payers: Maintain clear communication to address recurring denial patterns.
The Financial and Operational Impact of Denials
According to the American Hospital Association, U.S. hospitals spent an estimated $19.7 billion in 2022 appealing claims that were denied. Each appeal cost an estimated $43.84, adding work and time to the revenue cycle.
Practices that implement structured denial workflows can reduce avoidable rework, support more timely follow-up, and strengthen visibility into cash flow.
How AI Is Transforming Denial Management
Automation tools, including denial prediction and robotic process automation, are changing how billing teams handle denials. An AKASA survey reported that 74% of hospitals and health systems used automation in revenue cycle operations.
Experian Health reported that adoption of AI for denial reduction remained limited even as providers expressed optimism about its potential.
- Predictive analytics: Identify high-risk claims before submission.
- Faster processing: Automate selected charge-entry, remittance, and follow-up tasks.
- Fewer manual errors: Reduce repetitive data-entry mistakes that can contribute to rejections.
- Real-time insights: Monitor denial trends and workflow performance through dashboards.
Why Outsource Denial Management
For many practices, managing denials in-house can be time-consuming and resource-heavy. Outsourcing to a medical billing company can provide dedicated RCM support, workflow technology, and denial analytics without adding internal payroll burden.
- Specialized expertise: Billing professionals handle complex payer rules and denial categories.
- Focused follow-up: Dedicated teams manage corrections, resubmissions, and appeals.
- Technology access: Automation and analytics support claim review and trend monitoring.
- Compliance and security processes: Workflows should align with payer requirements and applicable privacy and security obligations.
Checklist Is Your Denial Management Process Working
- Denial trends are tracked regularly.
- Payer filing and appeal deadlines are monitored.
- Payer-specific patterns are analyzed.
- Eligibility, authorization, coding, and documentation issues are reviewed by root cause.
- Automation supports claim validation where appropriate.
- A/R days and recovery activity are monitored regularly.
Frequently Asked Questions
Can outsourcing reduce denial rates
Expert billing teams and workflow tools can help identify errors, prevent recurring denials, and support faster follow-up. Results depend on the practice, payer mix, processes, and contracted scope.
How do I recover denied claim revenue
Identify the denial, categorize the root cause, correct the issue, resubmit when appropriate, and appeal with documentation when required.
What should I do if my denial rate keeps rising
Track patterns, identify recurring causes, and implement a structured prevention and recovery workflow.
How can I prevent denials proactively
Verify coverage, track prior authorizations, audit coding and documentation, and use claim-scrubbing tools where appropriate.
Are there technology solutions for denial management
Yes. Claim scrubbing, automated eligibility checks, and analytics dashboards can support prevention and recovery workflows.
How long do I have to appeal a Medicare denial
The deadline depends on the type and level of appeal. Verify the instructions on the decision notice and current CMS guidance before filing.
The Bottom Line
Denial management is about revenue protection. A structured workflow that combines front-end validation, coding and documentation review, timely correction, targeted appeals, and trend monitoring can help practices recover eligible revenue and prevent recurring errors.
To discuss your current denial patterns and recovery workflow, contact Dastify Solutions.
Disclaimer and Editorial Standards
This article is for informational purposes only and is not billing, coding, legal, medical, payer-contract, or financial advice. Denial trends, payer policies, coding requirements, and CMS rules change frequently. Verify current requirements through the applicable payer, current code-set resources, CMS guidance, and your contracts before acting. Outcomes vary by specialty, payer mix, claim volume, documentation, and workflow; results are not guaranteed.


